
Root Canal Treatment · Murrieta, CA
Root Canal Treatment in Murrieta: Do You Actually Need One?
Two words people dread, attached to the one procedure that ends a toothache instead of starting one.
I'm Dr. Bao Nguyen. I do root canals myself, in the same chair where I examined you, and often on the same day you walk in hurting. I'll also tell you when you don't need one, which happens more often than most people expect.
The short answer
Do I need a root canal?
You need a root canal when the nerve inside a tooth is infected or dying and can't recover, which usually shows up as pain that lingers after something hot or cold, a toothache that wakes you at night, swelling or a pimple on the gum, or a tooth turning gray. You probably don't need one for a quick zing of cold that's gone in a second or two, a cracked tooth whose nerve still tests healthy, or soreness from clenching or a sinus infection. A pulp test and a digital X-ray tell the two apart, and at my Murrieta office that's part of a $20 exam, with the root canal often done the same day if you need it.
Root canal treatment at a glance
- Procedure
- Root canal therapy, also called endodontic treatment: removing infected or inflamed pulp, disinfecting and sealing the canals, then crowning the tooth
- Who does it
- Dr. Bao Nguyen, DDS, in-house at Promenade Dental Care; complicated cases referred to an endodontist
- Visits
- Usually one, with a same-day CEREC crown
- Chair time
- Under an hour for a front tooth, 60 to 90 minutes for a molar, plus about an hour for the crown
- Anesthesia
- Local anesthetic; nitrous oxide on request
- Recovery
- Tender for two to five days; over-the-counter pain relievers for most people
- Success
- About 95 percent long term when the tooth is crowned
- Cost
- $20 exam with digital X-rays; written estimate before treatment; same-day crowns start at $1,200 cash
- Insurance
- In network with Delta Dental PPO, Cigna, MetLife, Guardian, Aetna and United Concordia; CareCredit financing
- Where
- 26957 Date St, Suite 204, Murrieta, CA 92563 · (951) 412-0127
What the procedure is
What is a root canal, in plain English?
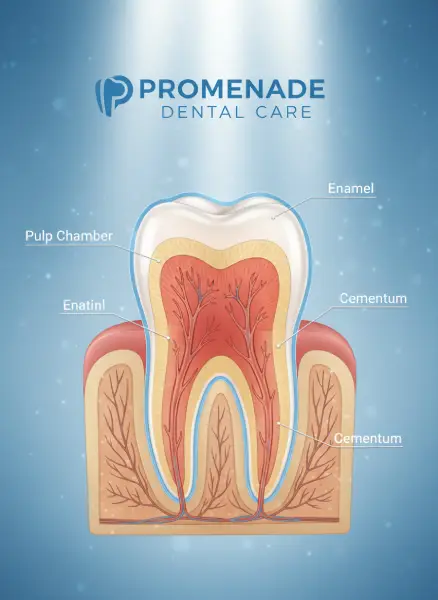
Every tooth is hollow in the middle. Under the enamel and the dentin sits a small chamber of living tissue called the pulp. It holds the nerve and the blood supply that built the tooth while it was growing, and it runs down each root in thin channels called canals. Here's the part most people never hear: once a tooth is fully formed, it doesn't need that pulp anymore. The bone and ligament around the root keep the tooth in place and working long after the pulp is gone.
Trouble starts when bacteria get into that chamber, usually through deep decay, a crack, a large filling that's been redone a few times, or an injury from years ago. Inflamed pulp is trapped inside hard walls, so it can't swell the way a cut finger does. Pressure builds, the tissue dies, and the infection works down the root into the bone at the tip, where it forms an abscess. That's where the throbbing, the facial swelling and the occasional emergency room visit come from.
A root canal removes that pulp. I clean out the canals, disinfect them, fill them with a rubbery, biocompatible material called gutta-percha, and seal the tooth. Then a crown goes on to protect it, and in my office that's usually a CEREC same-day crown milled while you wait. The American Association of Endodontists counts more than 15 million root canals a year in the United States. It's one of the most routine procedures in dentistry, even if it has the worst reputation.
Why the timing matters
An infected nerve isn't a problem that holds still. Every week you wait, the abscess widens and the tooth gets harder to rebuild. A tooth that needed a root canal in March can need an extraction, a graft and an implant by June.
For someone in Murrieta lying awake at two in the morning with a throbbing molar, the practical question is how fast you can get numb. The shortest route runs through my office on Date Street, not a referral waitlist forty minutes up the freeway.
Who needs it
Who needs a root canal? The symptoms and conditions
Not every toothache is a nerve problem, and I'll cover the ones that aren't in the next section. These are the symptoms that usually mean infection or inflammation has already reached the pulp. Once it has, the window for a simple filling has closed. The Mayo Clinic's guide to tooth abscesses lists most of the same warnings.
The conditions behind those symptoms
In diagnosis terms, a root canal treats three situations. The first is symptomatic irreversible pulpitis: a nerve that's still alive but too inflamed to heal. The second is pulp necrosis: a nerve that has already died, often with apical periodontitis, which is inflammation in the bone at the root tip that shows up as a dark area on the X-ray. The third is an abscess at the root tip, sudden and swollen or slow and draining. Those are the categories in the American Association of Endodontists' diagnostic terminology, and I use them in my chart notes so the record means the same thing to any specialist who sees your tooth later. The Cleveland Clinic's pulpitis overview explains the reversible-versus-irreversible difference well if you want a second source.
What raises the odds of needing one
Most of the root canals I do trace back to four causes, and all four are at least partly in your control. Deep decay is the big one: sugar and acidic drinks feed the bacteria that tunnel through enamel, and once a cavity reaches the pulp a filling can't save the nerve. Clenching and grinding come next, because a tooth that flexes under that load night after night eventually cracks and lets bacteria in. Tobacco and heavy drinking round it out. Smoking makes gum infection around the root more likely, and alcohol dries the mouth, which lets decay move faster than saliva can fight it. The National Institute of Dental and Craniofacial Research has a good plain-language page on how decay gets started.
- Keep sugary and acidic drinks to mealtimes, and rinse with water afterward so acid isn't sitting on the enamel for hours.
- Brush twice a day, floss once, and keep your six-month exams. A cavity I catch on an X-ray is a filling. One you can feel is often a root canal.
- If you wake with a sore jaw, or your molars look flat and worn, ask me about a night guard before one of them cracks.
- Quit tobacco, and if you drink, stay hydrated. A dry mouth loses the saliva that normally washes bacteria off the teeth.
Recognize any of these?
Call (951) 412-0127 and come in for a $20 exam with digital X-rays. I can tell you in one visit whether the nerve is involved, and in many cases start the root canal the same day rather than sending you home to come back while the tooth still hurts.
If the chair itself is what's keeping you away, ask about nitrous oxide when you call.

When you don't need it
When don't you need a root canal?
This is the section I wish more dental websites had. A lot of tooth pain isn't coming from the nerve at all, and a root canal on a healthy nerve is a procedure you didn't need and can't undo. One patient wrote in a Google review that I'd advised against treating things good home care could handle. That's the job. Here are the look-alikes I see most often in Murrieta and what I do about them instead.
| What you notice | What it usually is | What I usually do instead |
|---|---|---|
| A quick zing from cold that's gone in a second or two | Worn enamel, an exposed root surface, or a small cavity. The nerve is irritated but healthy. | Desensitizing toothpaste, fluoride, bonding over an exposed root, or a small filling. More on sensitive teeth. |
| A deep cavity, but the pain stops when the cold does and the nerve tests normal | Reversible pulpitis. The nerve can recover once the decay is out. | A deep filling, and a recheck if the tooth is still touchy in a few weeks. |
| An ache after a new filling or crown that's a little better each week | A nerve settling down after being worked on | Time. If the bite feels high, a few minutes of adjustment. |
| A sharp jab when you let go of a bite, with a nerve that still tests healthy | A cracked tooth | Usually a crown. Most cracked teeth never need a root canal. |
| Several upper back teeth aching at once during a cold or allergy flare, worse when you bend over | Sinus pressure on the roots of the upper teeth | Treat the sinus. If the ache outlasts the congestion, come back and I'll test the teeth. More in why do my teeth hurt. |
| Several sore teeth and a tired jaw first thing in the morning | Clenching or grinding at night | A custom night guard, and a TMJ evaluation if the jaw joint is involved. |
| A swollen gum next to a tooth whose nerve tests alive, with a deep pocket beside it | A gum (periodontal) abscess, not a nerve infection | Clean and drain the pocket, then gum disease treatment or a deep cleaning. |
| A root split top to bottom, too little tooth left to hold a crown, or severe bone loss | A tooth a root canal can't save | Extraction and a plan to replace the tooth. I'll say so plainly. |
Two things I won't do. I won't start a root canal before the tests show the nerve can't recover, and I won't hand you antibiotics in place of treatment. The American Dental Association's antibiotic guideline recommends against antibiotics for an inflamed or dying nerve in healthy adults, because they can't reach the problem inside the tooth. They're for an infection that's spreading, with fever or swelling beyond the tooth, and I prescribe them when that's what I see.
If your pain fits one of the rows above, the $20 exam is still worth it. The point is to rule the nerve out with tests, not with hope.
What happens
What happens during a root canal, step by step?
Five steps, in order, after the diagnosis is settled. I talk you through them as I go if you'd rather know than wonder, and I keep quiet if you'd rather listen to a podcast.
1Numbing and isolation
Topical gel first, so the injection is barely noticeable. Then I numb the tooth completely and wait until it's numb before starting. A thin rubber sheet called a dam goes over the tooth to keep saliva and bacteria out. Nitrous oxide is there if you want it.
2Opening the tooth
I make a small opening through the top of the tooth to reach the pulp chamber. From here on you should feel pressure and vibration, never sharpness. Raise a hand and I stop and add anesthetic.
3Cleaning and shaping
Fine, flexible files remove the pulp from each canal while a disinfecting rinse flushes out bacteria. An electronic apex locator measures each canal to its tip. Missed canals are a leading cause of failure, so I find and verify every one before moving on.
4Filling and sealing
The dried canals are filled with gutta-percha and a sealer, which closes them off from bacteria. If the crown is going on another day, a temporary filling seals the opening until then.
5The crown
A treated back tooth gets brittle and needs a crown. I scan the tooth, design the crown and mill it in the office with CEREC, then bond it the same visit, so most patients leave with the permanent crown on.
A front tooth with one canal usually takes under an hour. A molar with three or four canals takes 60 to 90 minutes, and the same-day crown adds about another hour. When an infection is large and active, I sometimes split treatment into two visits so the tissue can settle, but that's the exception rather than the rule.
Does a root canal hurt?
The reputation is worse than the reality, and it's worth knowing where the reputation came from. Most of those stories are decades old, from an era of weaker anesthetics. In an American Association of Endodontists survey, people who'd actually had a root canal were six times more likely to call it painless than people who'd only heard about one.
The injection is the most eventful part. After that it's pressure, vibration and the odd taste of the rubber dam. Plenty of people put in earbuds. A few fall asleep. One patient finished a whole episode of her show and was surprised when we told her we were done.
Keep the comparison honest, though. The choice isn't between a root canal and no pain. It's between a root canal and the toothache you already have.
How Dr. Nguyen diagnoses it
How do I decide a tooth really needs a root canal?
No single test settles it. The AAE's diagnostic guidance makes the same point: you put the patient's story, the clinical tests and the X-ray together and look for agreement. That's how I work. When two findings disagree, I don't start a root canal. I re-test, take another image, or watch the tooth for a couple of weeks if it's safe to wait.
First, the story
Before I touch the tooth, I ask what sets the pain off, how long it lasts once it starts, whether it wakes you up, whether you can point to one tooth, and whether anything changed recently, like new dental work, biting down hard on an olive pit, or a head cold. A pain that's gone the moment the cold is gone tells me something very different from one that's still aching a minute later.
Then the tests
- Cold test
- A cold stimulus on the tooth, compared with a healthy tooth nearby. A short response that fades is normal. Pain that lingers suggests a nerve too inflamed to heal. No response at all suggests a nerve that has died.
- Electric pulp test
- A small, gentle current that checks whether the nerve responds at all. Useful when the cold test is unclear.
- Tapping and pressing
- Tenderness to a light tap, or to pressing on the gum over the root tip, points to inflammation in the bone at the end of the root.
- Bite test
- Biting on a small stick one cusp at a time. Pain when you let go is how a crack gives itself away.
- Gum probing
- A deep, narrow pocket on one side of a tooth can mean a split root or a gum problem rather than a nerve problem.
- Digital X-rays
- Show how deep the decay goes, how close old fillings sit to the nerve, the number and shape of the canals, and any dark area at the root tip. You see them on the screen with me.
- 3D cone-beam scan
- When a flat X-ray doesn't explain the symptoms, an in-office cone-beam CT shows the roots and bone in three dimensions, including canals and lesions a 2D image can hide.
- Intraoral camera
- A close-up photo so you can see the crack, the broken filling or the decay I'm describing.
Putting it together
| What the tests show | What I call it | What I recommend |
|---|---|---|
| A short response to cold that fades, no tenderness, a clean X-ray | A normal or reversibly irritated nerve | No root canal. A filling, or nothing at all. |
| Cold pain that lingers, or aching with no trigger, and the nerve still responds | Symptomatic irreversible pulpitis | A root canal, or extraction if the tooth can't be restored |
| No response to cold or electric testing, often a dark area at the root tip | Pulp necrosis, often with apical periodontitis | A root canal, even if the tooth doesn't hurt yet |
| Swelling, a gum boil, a tooth that's tender to tap | An acute or chronic apical abscess | Drain it and start the root canal; antibiotics only if the infection is spreading |
| A tooth that already had a root canal and hurts again | A previously treated tooth | X-rays and possibly a 3D scan, then retreatment, root-tip surgery, or referral to an endodontist |
Then I show you the X-ray and tell you which row you're in. If it's the first row, you get a filling or a clean bill of health, not a root canal.
Who's doing the testing
I'm Dr. Bao Nguyen. I graduated from the UCLA School of Dentistry, then completed an Advanced Education in General Dentistry residency with the U.S. Navy at Naval Hospital Camp Pendleton, where root canals were part of the everyday caseload. Active duty Marines weren't sent across town to civilian specialists. The residency-trained dentist diagnosed the tooth and did the root canal, often the same day the Marine showed up hurting. I served ten years in the Navy Dental Corps, including deployments to Kuwait and Iraq, and opened Promenade Dental Care in 2010.
That adds up to 26 years of clinical practice. I take about 40 hours of continuing education a year and belong to the American Dental Association, the California Dental Association and the Tri-County Dental Society. My approach is conservative: I'd rather keep your natural tooth, and I recommend only the treatment the tests support.
When a case runs past general-practice endodontics, such as severely calcified canals, a complicated retreatment, or an apicoectomy on a stubborn back tooth, I refer to an endodontist I trust and manage the handoff myself. Between me and my team, we can walk you through it in English, Spanish or Vietnamese.

Cost
How much does a root canal cost in Murrieta?
Here's what I can put a number on. The exam that tells you whether you need a root canal is $20, digital X-rays included. The same-day CEREC crown that finishes most back-tooth root canals starts at $1,200 cash. Those are published fees, and you'll see the same figures on my dental exam and same-day crowns pages.
$20
Exam with digital X-rays
Diagnosis and a written estimate, usually the same day
$1,200
Same-day CEREC crown, cash
Starting fee. Milled and bonded at the same visit
I don't post one price for the root canal itself, because it depends on the tooth. Front teeth usually have a single canal and cost the least. Premolars have one or two. Molars have three or four, take longer, and cost more. A tooth that's been treated before, or one with a large active infection, takes more time again. So after the exam you get one written estimate covering the root canal and the crown together, and the number on that estimate is the number you pay.
One piece of arithmetic is worth spelling out. A root canal and crown almost always cost less than the full extraction route: pulling the tooth, a bone graft if the socket needs one, a dental implant, the abutment and the implant crown. That route also runs three to nine months instead of one or two visits. Saving the tooth usually saves the calendar and the wallet at the same time.
No insurance? Call (951) 412-0127 and ask what a root canal and crown cost in cash for the kind of tooth that's bothering you. You'll get a firm number in writing after the exam, with no surprise line items later. CareCredit financing is available, with up to six months at no interest for qualified applicants.
Insurance
Does dental insurance cover a root canal?
Usually, in part. We're in network with Delta Dental PPO, Cigna, MetLife, Guardian, Aetna and United Concordia. Most PPO plans pay somewhere between 50 and 80 percent of a root canal after the deductible. Some plans file it as a basic service and some as a major one, and that one detail changes your share more than anything else. Crowns are almost always in the major category, commonly at 50 percent. Because we're in network with those plans, your share here is often lower than it would be at an out-of-network endodontic specialist.
A few things catch people off guard. The annual maximum, often in the $1,000 to $2,000 range, can go quickly when a root canal and a crown land in the same year. Some plans have a waiting period before major services are covered on a new policy. And many plans limit how often they'll pay to replace a crown, often once every five years.
That's why my front office verifies your benefits before treatment and gives you your share in writing. I can't quote an insured fee before that, because it depends on your plan's percentage, your deductible and what's left of your maximum. If your plan isn't on the list above, call and ask how it would work here. If you don't have insurance, the cash fees above apply, and CareCredit can spread the cost.
Risks and limitations
What are the risks and limits of a root canal?
A root canal is one of the most predictable things I do, but it isn't a guarantee, and you should hear the downsides from me before you hear them from the internet. The Cleveland Clinic's root canal page covers the same list from a medical center's point of view.
- It can fail. In a study of nearly 1.5 million teeth treated under one national insurer, 97 percent were still in the mouth eight years later. The ones that fail usually trace back to a canal that wasn't found, a seal that leaked, new decay, or a crack. Retreatment or surgery at the root tip can often still save the tooth.
- The tooth gets more brittle. A back tooth without its pulp, and without a crown, is at real risk of splitting. In one long-term study, root canal teeth left without a crown were lost about six times faster than crowned ones. That's why I crown back teeth, usually the same day.
- A flare-up can happen. A small share of patients have a few days of more pain or swelling after treatment, more often when the tooth was very painful or infected going in. It settles with care, and my root canal recovery guide explains what's normal and when to call.
- Rare technical problems. In narrow or sharply curved canals, a file can break or the canal can be hard to reach all the way to the tip. Upper molar roots sometimes sit close to the sinus. When the X-ray or the 3D scan shows a tooth with those odds stacked against it, I tell you before we start, and I may refer it to an endodontist.
- Front teeth can darken. A treated front tooth can slowly turn a shade darker over the years. It's cosmetic, and bonding or a crown can cover it.
- It can't fix everything. A root canal treats the inside of the tooth. It doesn't repair a root that's split, replace bone lost to gum disease, or rebuild a tooth with too little left to hold a crown.
One thing that isn't a risk is illness somewhere else in the body. That idea comes from early-1900s research that was discredited long ago, and the AAE's page on root canal myths walks through why.
Alternatives
What are the alternatives to a root canal?
Once a nerve can't recover, there are really two paths: treat the canals or take the tooth out. Most of this list is a version of the second path.
- Extraction and an implant. The closest thing to a new tooth. It takes three to nine months from extraction to final crown, and it costs more. I place single dental implants here.
- Extraction and a bridge. Faster than an implant, but the teeth on either side get reshaped for crowns. My bridge vs. implant page compares the two.
- Extraction and a partial denture. The least expensive replacement, and the least like a real tooth.
- Extraction and nothing. Cheapest today. Over time the neighbors drift and the opposite tooth grows into the gap, which can turn one missing tooth into a bite problem.
- Vital pulp therapy, for some teeth. When a nerve is inflamed but still alive, removing only the damaged part and sealing the rest is an option in some cases, mostly in younger teeth. If your tooth looks like a candidate, I'll talk it through with you.
- Antibiotics, or waiting. Neither is an alternative. Antibiotics can't reach a dying nerve inside the tooth, and a nerve with irreversible pulpitis doesn't heal on its own.
| Factor | Root canal + crown | Extraction + implant |
|---|---|---|
| Natural tooth kept | Your own root stays in the jaw | The root is removed entirely |
| Jawbone health | The natural root keeps stimulating the bone as you chew | An implant preserves bone; an unfilled gap lets it shrink |
| Timeline | One to two visits, often same day with a CEREC crown | Three to nine months: extract, heal, place, integrate, crown |
| Neighboring teeth | Untouched | Untouched with an implant; a bridge would mean reshaping them |
| Long-term success | About 95 percent at 10 years with a crown | About 95 percent for implants at 10 years |
| Relative cost | Lower overall | Higher: extraction, graft if needed, implant, abutment, crown |
| How it feels | Full natural bite feedback; you sense pressure normally | Full function, without a real root's pressure sense |
Each choice has its moment. I'm not trying to talk you into either one. I'm trying to pick the option that still looks like the right call ten years from now, and when a tooth belongs out, I'll tell you that and send you to my tooth extraction page rather than sell you a root canal.
Recovery
What is recovery like after a root canal?
Shorter than most people expect. The numbness wears off in a few hours. The tooth and the gum around it are usually tender for two to five days, because the tissue at the root tip was inflamed before I ever started. Over-the-counter ibuprofen or acetaminophen, taken as the label directs, covers it for most people. When the starting infection was severe, I may prescribe something stronger.
You can drive yourself home after local anesthetic or nitrous oxide. Most people are back at work the next day. Wait until the numbness is gone before you eat, and if you left with a temporary filling instead of the permanent crown, chew on the other side until the crown is on.
Call me at (951) 412-0127 if the swelling gets bigger instead of smaller, if the pain is worse on day three than on day one, if the tooth feels tall when you bite, or if a temporary filling comes out. Facial swelling that spreads, a fever, or any trouble swallowing or breathing means the emergency room first.
The thing patients mention most the morning after isn't the tooth. It's that they slept through the night for the first time in a week. For the day-by-day version, including what's normal on day two versus day five, read my root canal recovery guide.
What patients say
What do Murrieta patients say about their root canals?
Absolutely the best care! I became a patient in July of last year and needed some emergency dental work. I was able to get in the same day and have a crown and root canal done with zero pain! I recently had another toothache and was again provided a prompt same day appointment. Hands down the best dental experience I’ve had! Zero pain, zero wait time, and very quick care. Pricing is always up front and affordable also.
— Alicia Alvarado · Google Review
Dr. Nguyen is a wonderful dentist. Very friendly and compassionate. Very skilled. I had a root canal done in less than 2 hours with the crown completed the same day. WOW!!!
— Same-day restorative patient · Google Review
I saw doctor Bao Nguyen at Promenade Dental Care on three occasions. In these visits, Dr Nguyen took time to carefully examine my dental concerns and explained very clearly to me what my conditions are, and what treatment options available. He advised me against immediate treatments for conditions that can be improved or maintained with good oral hygiene. He was very gentle with treatments, especially with the local anaesthetic injections. Greatly appreciate his professional care.
— C. Nguyen · Google Review
I’ve been to a lot of different dentists through the years and have had several fillings/crowns done. I often times experience pain and pressure during procedures even after the anesthetic. This time, zero pain, zero pressure, no nonsense. I’ll be coming back for regular cleanings and any needed procedures. They have my business indefinitely!
— Dominic S. · Google Review
Very knowledgable and good prices. Does only what is necessary. Does not just look for stuff to charge for. Got an appointment quickly when I thought it was an emergency. My favorite dentist ever!!
— Sheila O’Connor · Google Review
I called Dr. Nguyen very early on a Saturday morning with an emergency. He fit me in first thing. I watched him use a computer to create a new crown — it was fascinating. Whether you need routine care or urgent attention, you can trust this man to deliver exceptional service.
— Lisa C. · Google Review
FAQ
Root canal questions I get asked most
Does a root canal hurt?
No, and I say that as the person holding the handpiece. The tooth is completely numb before I open it, so what you feel is pressure and vibration, not pain. Most of my Murrieta patients tell me afterward that it felt like a long filling. If you feel anything sharp, you raise a hand and I stop and add more anesthetic. That rule doesn't change. The pain people connect with root canals is almost always the infection they walked in with, not the treatment that removed it. The tooth is usually tender for two to five days afterward, and ibuprofen handles that for most people. The American Association of Endodontists has found that patients who've actually had a root canal are about six times more likely to call it painless than people who've only heard the stories.
How long does a root canal take?
A front tooth with one canal is usually done in under an hour. A molar with three or four canals runs 60 to 90 minutes, because every canal has to be found, measured, cleaned and sealed on its own. If I place a same-day CEREC crown right afterward, add about another hour for the scan, the design, the milling and the bonding. Most patients at Promenade Dental Care sit down once and leave with the root canal finished and the permanent crown already on.
Can a root canal be done in one visit?
Usually, yes. I do the root canal and mill the CEREC crown in the same office on Date Street, so most patients finish the diagnosis, the treatment and the permanent crown in one appointment. When a tooth has a large, active infection I sometimes split the work across two visits so the tissue can settle first, but that's the exception. A one-visit finish matters most when the tooth is still sore and the last thing you want is another trip back.
Do I need a crown after a root canal?
On a back tooth, almost always. A treated tooth has lost its blood supply from the inside and gets more brittle over the years, and a full-coverage crown is what keeps it from splitting. One long-term study found that root canal teeth left without a crown were lost about six times faster than crowned ones. I design, mill and bond a ceramic CEREC crown the same day, so you leave protected instead of wearing a temporary for two or three weeks. A front tooth with very little damage can sometimes get by with a bonded filling, and I'll tell you if yours is one of them.
Is a root canal better than pulling the tooth?
If the tooth can still be restored, saving it is almost always the better choice. Your own root keeps stimulating the jawbone, you skip the three-to-nine-month timeline of an extraction and implant, and you keep the natural pressure feedback only a real root gives you. Extraction is the honest answer when a tooth has a vertical root fracture, severe bone loss around it, or too little structure left to hold a restoration. I look at your X-rays and tell you which one you actually have. I won't talk you into a root canal on a tooth that belongs out, and I won't pull a tooth I can still save.
How much does a root canal cost in Murrieta?
It depends on the tooth. A single-canal front tooth costs the least, and a three- or four-canal molar costs more because there's more to clean and seal. The crown that protects the tooth afterward is a separate fee, and my same-day CEREC crowns start at $1,200 cash. The exam that tells you whether you need any of it is $20 with digital X-rays, and afterward you get one written estimate covering the root canal and the crown together. The number on that estimate is the number you pay. We're in network with Delta Dental PPO, Cigna, MetLife, Guardian, Aetna and United Concordia, and CareCredit financing is available. Call (951) 412-0127 and we'll tell you what it runs for your type of tooth.
Does dental insurance cover root canals?
Most PPO plans pay 50 to 80 percent of a root canal after the deductible, depending on whether your plan files it as a basic or a major service and which tooth it is. Crowns are usually covered as major work, commonly at 50 percent. We're in network with Delta Dental PPO, Cigna, MetLife, Guardian, Aetna and United Concordia, so your share here is often lower than it would be at an out-of-network endodontic specialist. My front office verifies your benefits before treatment and gives you your out-of-pocket cost in writing before I pick up an instrument.
How soon can I get a root canal appointment in Murrieta?
We hold same-day and next-day openings for patients in real pain, so call (951) 412-0127 first thing if you can. In many cases I can examine you, take digital X-rays, confirm the diagnosis and start the root canal in that same visit. That's the practical reason I keep root canals in-house: you aren't waiting two weeks for a specialist appointment while an abscess gets bigger.
Can a root canal fail?
It can, but it isn't common. Large studies put long-term tooth survival after a root canal in the mid-to-high 90s, percent-wise. When one does fail, it usually traces back to a canal that was never found, a seal that broke down over time, new decay, or a crack in the tooth. Caught early, retreatment often saves it. When retreatment isn't enough, the remaining options are surgery at the root tip, called an apicoectomy, or extraction. I check treated teeth with X-rays at your regular visits, so problems turn up while they're still fixable.
How long does a root canal last?
Decades, when the tooth gets a crown and normal care, and many root canal teeth last the rest of a patient's life. What shortens that lifespan is predictable: skipping the crown, new decay at the edge of the crown, or clenching and grinding that cracks the tooth. Brush and floss the treated tooth like any other, keep your checkups so I can watch it on X-ray, and wear a night guard if you grind.
Can I drive myself home after a root canal?
Yes, if you had local anesthesia only, which is the standard. You can drive, go back to work, and eat once the numbness wears off. Nitrous oxide clears your system within minutes, so patients who choose it usually drive themselves too.
What can I eat after a root canal?
Wait until the numbness is completely gone before you eat anything, so you don't bite your cheek or tongue. If you left with a same-day CEREC crown, the tooth is fully restored and you can eat normally, though most people prefer softer food for a day while the tenderness settles. If you left with a temporary filling instead, chew on the other side and skip anything sticky or hard until the crown is bonded. Warm salt water rinses feel good for the first couple of days.
What is the most common sign that you need a root canal?
Pain that doesn't go away on its own. A tooth that aches for days, throbs at night, or gets worse instead of better is the classic picture of a pulp that's infected or dying. Sensitivity to heat or cold that lingers for a minute or more is the second thing patients describe most. Both are different from the quick zing of cold that fades in a second or two, which usually points to enamel wear or a small cavity rather than a nerve problem. Swelling, a bump on the gum, pain when you bite, and a tooth turning gray are the other signs I look for, and any of them is a reason to call.
When should I see a dentist about tooth pain?
Call the same day if the pain has lasted more than a day or two, if it wakes you at night, if it hurts to bite, or if you notice swelling, a pimple on the gum, or a tooth changing color. Those are nerve-level symptoms and they don't resolve on their own. Facial swelling, fever, or any trouble swallowing or breathing is an emergency: go to the ER first and call us afterward. A tooth that's only briefly sensitive to cold can wait for a regular exam, but don't put it off. I'd much rather fix a cavity than a nerve.
What happens if I ignore a tooth that needs a root canal?
It gets worse, not better. The infection works into the bone around the root, the abscess grows, and the tooth gets harder to save with every week that passes. As that bone goes, the neighboring teeth lose support and can start to drift, so one neglected molar can turn into a bite problem. What started as a straightforward root canal becomes an extraction, and that extraction may need a bone graft before an implant is even possible. In rare but well-documented cases, a dental infection spreads to the jaw, neck, airway or bloodstream and becomes a medical emergency. If your face is swelling or you're having trouble swallowing or breathing, go to the emergency room rather than waiting for morning.
Do root canals cause illness elsewhere in the body?
No. That claim traces back to the focal infection theory, research from the early 1900s that used methods no laboratory would accept today and that was discredited long ago. There's no credible evidence linking root canal treatment to cancer, heart disease or any other systemic illness, and the American Dental Association and the American Association of Endodontists are both clear on the point. The real health risk runs the other way: leaving an infected tooth untreated keeps live bacteria sitting in your jawbone.
Why do you perform root canals in-house instead of referring me to an endodontist?
Because my training prepared me to, and because keeping it under one roof is better for the patient. I completed an Advanced Education in General Dentistry residency at Naval Hospital Camp Pendleton, where root canals were part of the everyday caseload. Active duty Marines weren't sent across town to civilian specialists. Doing the diagnosis, the root canal and the crown in one office means one set of X-rays, one estimate, and often one appointment. When a case genuinely runs past general-practice endodontics, such as severely calcified canals, a complicated retreatment, or an apicoectomy on a difficult back tooth, I refer you to an endodontist I trust and handle the coordination myself.
What is the difference between a root canal and a deep filling?
Whether the nerve inside the tooth is still alive and able to recover. If the decay is deep but the pulp can heal, a condition called reversible pulpitis, a deep filling is enough. Once bacteria have infected or killed the pulp, that's irreversible pulpitis or pulp necrosis, and no filling will fix it. The diseased tissue has to come out. That's why I confirm the diagnosis with cold and electric pulp testing plus digital X-rays before recommending either one. Treating the wrong condition wastes your money and puts you right back in the chair.
Can a tooth need a root canal even if it doesn't hurt?
Yes, and it's more common than people expect. A nerve can die quietly after an old injury or under a deep filling, and the infection that follows can sit at the root tip for months without much pain. I usually find these on a routine X-ray as a dark area at the end of the root, in a tooth that no longer responds to cold or electric testing. Treating it before it flares is easier on you than waiting for the swelling. The reverse is true too: a tooth that hurts a lot isn't automatically a root canal, which is why I test before I recommend anything.
Tooth pain that won't let up?
Book a $20 exam with digital X-rays. I'll find the problem, tell you honestly whether you need a root canal, and give you a written estimate before anything is done. Same-day and next-day openings are held for patients in pain.
Request an appointmentPromenade Dental Care · Dr. Bao Nguyen, DDS
26957 Date St., Suite 204, Murrieta, CA 92563, near Clinton Keith Road, minutes from the I-15 and I-215
Mon, Tue, Wed, Thu, Fri 8:00 AM–3:00 PM · Sat by appointment & emergencies · Sun closed
Serving Murrieta, Temecula, Menifee, French Valley, Winchester, Wildomar, Lake Elsinore, Canyon Lake, Fallbrook and Hemet